
Breast surgery
Direct-to-Implant Breast Reconstruction
Rebuilding the Breast in One Stage
Direct-to-implant (DTI) breast reconstruction is a one-stage breast reconstruction in which the permanent breast implant is placed at the time of mastectomy, avoiding the routinely planned tissue-expander stage. Dr. Lisa Cassileth began performing DTI reconstruction in 2007 and published her early one-stage technique in 2012.

Overview
When I began performing direct-to-implant breast reconstruction, implant reconstruction was routinely performed as a two-stage operation. A tissue expander was placed at the time of the mastectomy, and patients returned months later for another operation to remove the expander and replace it with a permanent implant. As skin-sparing and nipple-sparing mastectomy became more successful, I began questioning why every patient needed that second operation.
In many women, the breast skin and nipple were already being preserved. If the remaining skin envelope was healthy and could safely accommodate the desired breast volume, there was often very little that actually needed to be expanded. For example, if a patient ultimately needed a 250-cc implant and I could safely place a tissue expander at approximately that same volume during the first operation, why subject her to months with a temporary device and another surgery simply to exchange it for a 250-cc permanent implant? For patients already facing breast cancer treatment, chemotherapy, and multiple medical procedures, eliminating an unnecessary operation could make a meaningful difference.
That question led me to develop a one-stage approach in which the permanent implant could be placed at the time of the mastectomy and supported immediately. I began performing direct-to-implant reconstruction in 2007 and subsequently published our early experience with the technique.1 Direct-to-implant reconstruction has evolved considerably since then. Today, I perform most implant reconstruction above the pectoralis muscle and use modern mesh support, objective perfusion assessment, infection-prevention strategies, and a highly structured postoperative protocol. The goal is not simply to put in a permanent implant sooner. The goal is to perform the definitive reconstruction correctly from the beginning.
Why Tissue Expanders Became Less Necessary
Historically, tissue expanders made sense because mastectomy often removed a large amount of skin. Surgeons genuinely needed to recreate a breast envelope before placing a final implant. Skin-sparing and nipple-sparing mastectomy changed that equation. In many patients, the nipple and breast skin are preserved. The breast tissue is removed, but the envelope needed to create the new breast is already present. If the skin is already there, what exactly are we expanding?
When the mastectomy skin is healthy and the implant can appropriately fill the existing breast envelope, there may be no need for a temporary expander at all. Modern systematic reviews have confirmed that DTI reconstruction can be performed with acceptable complication rates in appropriately selected patients.2,3
Are Tissue Expanders Safer?
Patients are still frequently told that a tissue expander is the “safer” option after mastectomy. I think this deserves a more precise explanation. A tissue expander can give the surgeon flexibility when an area of mastectomy skin is clearly unhealthy and needs to be removed. Its size and shape can be adjusted if the final skin envelope changes unexpectedly. That is different, however, from assuming that a permanent implant automatically places harmful pressure on otherwise healthy mastectomy skin.
I do not believe that a properly selected and well-supported implant inherently causes mastectomy-flap necrosis. We specifically studied this question. In our series of 499 reconstructed breasts, patients whose implants were larger than their mastectomy specimens did not have a higher rate of mastectomy-flap necrosis. Necrosis was actually numerically lower in the upsized group, although the difference was not statistically significant.4
This challenges the assumption that placing an implant equal to, or even somewhat larger than, the volume of the original breast necessarily creates harmful pressure on the skin. A breast already occupied that skin envelope before mastectomy. If the reconstruction is appropriately sized and supported, replacing the removed tissue with an implant does not automatically create excessive tension simply because a permanent implant is being used. In our study, implant-to-specimen size difference did not independently predict flap necrosis; flap viability remained the more important issue.4
The Quality of the Mastectomy Matters
For me, successful direct-to-implant reconstruction begins before I ever place the implant. It begins with the mastectomy. DTI depends on preserving a healthy, well-perfused skin and nipple envelope, which is why I work closely with breast surgeons who understand that the mastectomy is inseparable from the reconstruction that follows it.
The thickness, blood supply, handling, and preservation of the mastectomy skin all affect the final result. I use intraoperative indocyanine-green angiography to provide an objective assessment of blood flow rather than relying on visual appearance alone. Systematic reviews have found that ICG-guided perfusion assessment can reduce mastectomy-flap necrosis and perfusion-related reoperation compared with clinical assessment alone.5 Specific perfusion thresholds are not absolute, but markedly reduced relative perfusion has been associated with a higher likelihood of tissue loss.6
This is one reason I believe reconstruction should be viewed as a team procedure rather than two unrelated operations performed by two different surgeons. When the mastectomy skin is healthy, DTI can be extremely predictable. When the skin is genuinely compromised, the safest reconstructive choice may be different. The goal is not to force every patient into a direct-to-implant reconstruction. The goal is to identify when a definitive reconstruction can be performed safely in one operation.
Why I Reconstruct Above the Muscle
Early implant reconstruction was commonly performed beneath the pectoralis major muscle. Over time, it became clear to me that this created several problems that could often be avoided. Placing an implant beneath the pectoralis requires detaching part of the muscle from the chest wall, which can increase postoperative discomfort and create animation deformity, where the implant visibly moves, flattens, pulls upward, or distorts when the pectoralis contracts.
Modern implants and mesh support allow many patients to avoid this entirely. By placing the implant above the muscle, I can preserve the pectoralis in its natural position while controlling the implant with structural mesh instead. This often allows a more natural relationship between the implant and chest wall and avoids muscle-related animation. In patients receiving postmastectomy radiation, recent evidence also suggests that prepectoral placement may reduce the risk of capsular contracture compared with subpectoral placement.7
Shape Force: Controlling Breast Shape, Not Just Implant Size
One of the biggest changes I have made in direct-to-implant reconstruction is a technique I call Shape Force. Many implant reconstructions use a standard mesh wrap in which two similarly shaped sheets are placed around the implant. The construct is essentially symmetrical. While this provides coverage and support, it can also encourage a very round breast shape and create a visible ridge or step-off where the upper edge of the implant meets the chest wall.
I began changing the way I constructed the mesh because I wanted greater control over that transition. With Shape Force, the mesh is not simply wrapped uniformly around the implant. It is intentionally tensioned differently in different parts of the breast. I make the construct narrower and more controlled at the upper pole and broader at the lower pole, then secure it to the chest wall at defined fixation points so that the implant maintains its intended position.
This allows me to influence how the implant itself sits. Instead of allowing the implant to determine the final breast shape, I use the mesh to help determine the implant's contour. For a patient who wants a very natural reconstruction, I can create a narrower upper pole and a fuller lower pole, producing a more gradual, teardrop-shaped transition from the chest wall. For a patient who prefers more upper-pole fullness and a rounder breast, the construct can be designed differently.
That means the conversation before surgery is no longer simply about breast size. It can also include breast shape. This is particularly important in thin patients, where there is very little subcutaneous fat over the chest wall and the borders of an implant can be much more visible. Controlling the upper-pole contour can make a significant difference in how natural the reconstruction looks, especially in low-cut clothing. I generally combine Shape Force with a highly moldable implant because the implant itself can respond to the forces created by the mesh. The goal is not to make every reconstructed breast look the same. It is the opposite: Shape Force gives the surgeon and patient more control over the contour of the reconstructed breast, allowing shape, not simply size, to become part of the reconstruction plan.
Structural Support Matters
I prefer structural mesh because I want the implant supported by deeper tissues rather than simply hanging within the mastectomy skin envelope. The purpose of reconstruction is not merely to fill the space where the breast used to be. The implant should be controlled. It should stay where it is intentionally placed and should not progressively descend simply because the overlying skin allows it to.
This is especially important in patients who began with loose or droopy breast skin. The mesh acts as an internal support system, helping establish implant position while also allowing me to control the contour of the reconstruction. In many patients, I want the implant to be more structurally supported than the natural breast was before mastectomy.
A Modern DTI Reconstruction Is a System
Direct-to-implant reconstruction is sometimes described as though the only difference is whether the surgeon places a permanent implant or a tissue expander. That is not how I think about it. Modern DTI in my practice is a system designed to reduce multiple potential sources of complications.
That begins with preservation of the mastectomy skin and continues through implant selection, structural support, perfusion assessment, infection prevention, bleeding reduction, wound management, and postoperative monitoring. Depending on the patient, this may include quantitative perfusion assessment, strict no-touch implant placement, local antibiotic delivery, perioperative tranexamic acid, careful drain management, closed-incision negative-pressure therapy, photobiomodulation, topical treatment to support compromised skin perfusion, hyperbaric oxygen therapy, and additional postoperative treatment directed at threatened mastectomy skin.
Several of these individual strategies have published support. Intravenous tranexamic acid has been associated with a substantial reduction in hematoma after implant-based breast reconstruction, including a large series in which hematoma decreased from 2.9% to 0.46%.8 Local antibiotic delivery using absorbable calcium sulfate has been associated with substantially lower infection-related expander or implant loss in published breast-reconstruction series.9,10 Closed-incision negative-pressure therapy has also been associated with lower wound-complication rates after prosthetic breast reconstruction.11,12
Photobiomodulation using red or near-infrared light is another component of our postoperative strategy. Experimental skin-flap literature suggests that photobiomodulation may improve microcirculation, angiogenesis, vascular density, and flap viability. A 2024 systematic review found improved flap survival in the large majority of included animal studies.13 Proposed mechanisms include effects on mitochondrial signaling, ATP production, nitric oxide signaling, reactive oxygen species, calcium signaling, cellular migration, and tissue repair.14 In our practice, photobiomodulation is delivered immediately postoperatively as an adjunct intended to support skin perfusion and wound healing.
Topical dimethyl sulfoxide, or DMSO, is another adjunct I use when skin perfusion is a concern. DMSO has been studied clinically in surgical skin flaps, including a prospective randomized mastectomy study in which topical treatment reduced flap-edge necrosis.15 Additional clinical studies have reported reduced wound-edge necrosis and successful use in threatened nipple-areolar ischemia.16,17 Proposed mechanisms include vasodilation, inhibition of platelet aggregation within injured microvasculature, antioxidant effects, and modulation of ischemia-reperfusion injury.
Hyperbaric oxygen has an established physiologic rationale and published clinical experience as an adjunct in compromised surgical flaps and ischemic breast-reconstruction tissue.18–20 By substantially increasing dissolved oxygen in plasma, HBOT can temporarily increase oxygen availability to hypoxic tissue while intrinsic perfusion recovers. It may also reduce edema and support angiogenesis, fibroblast activity, and wound healing.
No single maneuver eliminates complications. What matters is reducing risk at multiple points in the operation and recovery. Some improvements are major changes in technique. Others may improve outcomes only incrementally. But when many small improvements are combined, complications have fewer opportunities to develop.
Who Is a Good Candidate for Direct-to-Implant Reconstruction?
A good candidate for direct-to-implant reconstruction is not defined simply by having a small breast. I have performed DTI reconstruction across a very wide range of breast sizes. What matters more is the relationship between the skin envelope, nipple position, and the volume of the implant being placed.
I think of this as a hand-in-glove fit between the implant and the mastectomy skin. The implant should appropriately fill the available space without leaving excessive empty space around it.
Direct-to-implant reconstruction can work extremely well in smaller-breasted women, and many patients also want to be somewhat larger after reconstruction. If the skin envelope allows it, upsizing can be performed safely. Our implant-sizing study found no increase in mastectomy-flap necrosis when the implant was larger than the mastectomy specimen.4 In fact, a small-breasted patient who has extra skin from breastfeeding, pregnancy, weight change, or normal aging may sometimes achieve a better fit with a slightly larger implant than with an implant identical in volume to the original breast. The reason is simple: the implant needs to fill the available envelope appropriately. Too much empty space can create its own problems.
Large-breasted women may also be candidates for DTI. The limiting factor is often not the fact that the breast is large, but whether an implant is available that appropriately matches the desired breast volume and skin envelope. I have successfully performed DTI reconstruction in very large-breasted patients as well.
Nipple Position and Breast Droop Matter More Than Size
A more important limitation is significant breast droop or a very low nipple position. When the nipple position is only mildly low, some natural elevation can occur after mastectomy because the weight of the breast tissue has been removed and the implant is structurally supported. In selected patients, the reconstruction can also be designed so that the nipple and surrounding skin adhere in a somewhat higher position. If a patient is comfortable with a mildly low nipple position, DTI may still be an excellent option.
The challenge comes when a patient wants a substantial breast lift at the same time as reconstruction or when a very large breast is being reduced to a much smaller size. In those situations, the skin envelope may be much larger than the implant being placed, creating a mismatch between the implant and the available skin. The result can be loose skin, dead space, fluid accumulation, and a less predictable breast shape.
For that reason, patients with very low nipples or those who want to become substantially smaller may be better suited to a reconstruction that includes a formal lifting or skin-reduction technique. However, I do not exclude patients based on appearance alone. Each breast has to be evaluated individually. Many patients who initially appear to have too much skin or too much droop can still be candidates for direct-to-implant reconstruction once the skin envelope, nipple position, and desired final breast size are considered together.
The key question is not whether a breast is too small or too large for DTI. It is whether the implant and the mastectomy skin envelope can be matched closely enough to create a stable, well-supported reconstruction.
Does Direct-to-Implant Mean I Will Never Need Another Procedure?
Direct-to-implant reconstruction eliminates the routinely planned expander-to-implant exchange operation, but it does not mean that every patient will choose to have only one surgery in her lifetime.
Some patients are completely satisfied after their initial reconstruction. Others may later choose small refinements, most commonly fat grafting. Fat can be transferred from another area of the body to soften a visible implant edge, improve contour, correct a small asymmetry, or add additional soft-tissue coverage in a thin patient.
I consider this very different from a planned tissue-expander exchange. With a traditional two-stage reconstruction, the second operation is built into the treatment because the expander is temporary and must ultimately be replaced. With DTI, the implant placed at the mastectomy is intended to be the definitive implant. Any later procedure is based on the patient's anatomy, healing, or aesthetic goals rather than being an obligatory stage of reconstruction.
One of the goals of Shape Force is to create as smooth an upper-pole transition as possible during the initial reconstruction, potentially reducing the contour irregularities that often lead surgeons to recommend secondary fat grafting. This is a goal of the technique rather than a formally proven reduction in fat-grafting rates.
Direct-to-Implant Does Not Mean One Size Fits All
DTI is not appropriate for every patient. If the mastectomy skin is significantly compromised, if the nipple position requires a major lift, if the patient wants a very large reduction in breast volume, or if the skin envelope and desired implant cannot be matched reliably, another reconstruction may provide a better result. Those options may include a skin-reducing reconstruction, SWIM flap reconstruction, staged reconstruction, or another individualized approach.
The goal is never to perform DTI simply because it can be done. The goal is to choose the reconstruction that gives the patient the safest operation and the best long-term breast.
Nearly Two Decades of Evolution
My approach to direct-to-implant reconstruction has continued to evolve since I began performing it in 2007. The major changes have included eliminating the routine tissue-expander stage, developing immediate permanent-implant reconstruction, transitioning from subpectoral to prepectoral implant placement, increasing collaboration with mastectomy surgeons to protect flap viability, using quantitative intraoperative perfusion assessment, incorporating structural mesh support, developing Shape Force to control breast contour, improving infection-prevention strategies, adding advanced wound-management and perfusion-support techniques, and studying implant sizing and mastectomy-flap necrosis.
Some of the biggest improvements have come from major changes in technique. Others have come from many smaller decisions that each improve the odds by a little bit. Together, they have changed what direct-to-implant reconstruction can look like and how predictable it can become.
The Goal
Direct-to-implant reconstruction is not simply about avoiding a second surgery. It is about creating a definitive breast reconstruction from the beginning. That requires protecting the mastectomy skin, choosing the correct implant, controlling its position, controlling its shape, reducing preventable complications, and tailoring the reconstruction to the individual patient.
When all of those elements come together, the result can be a breast that is stable, supported, natural in appearance, and designed to remain that way long after the mastectomy is over.
What to expect
From consultation to recovery.
Before Surgery
- Consultation — Meet with Dr. Cassileth to review your anatomy, health history, and goals. 3D imaging helps visualize your expected outcome.
- Coordination — Our team works with your oncological surgeon to align the mastectomy and reconstruction into one procedure.
- Pre-op preparation — Medical clearance, lab work, and detailed instructions provided 2 weeks before surgery. Insurance authorization handled by our team.
During Surgery
- Mastectomy + reconstruction — Performed together under general anesthesia. Dr. Cassileth places the implant immediately after tissue removal — no expanders.
- Nerve reinnervation — When possible, nerves are reconnected to restore sensation over time.
- Pain management — Exparel nerve blocks are administered during surgery, providing pain relief for several days without narcotics, followed by Journavx, a non-opioid oral pain medication.
After Surgery
- First night — Most patients spend the first night at Immortelle, at an aftercare facility, or at home with a private-duty post-care RN.
- First week — Rest at home or in a recovery facility. Drains removed within 7–10 days. 24/7 access to our care team.
- Weeks 2–4 — Light activity resumes. Most patients return to desk work within two weeks.
- 6+ weeks — Full activity gradually reintroduced. Final results continue to settle over several months.
“Reconstructing the breasts at the same time as mastectomy eliminates the risks of multiple surgeries and, more importantly, helps minimize the sense of loss.”
Dr. Lisa Cassileth
“I am dedicated to helping women live with confidence and comfort. During your consultation appointment, we will discuss your medical history and your aesthetic goals and I will answer any questions you have. If you are not an ideal candidate for single-stage reconstruction with saline or silicone implants, I will guide you to a procedure that is right for your needs and goals.”
— Dr. Lisa Cassileth
Patient results
Real cases.
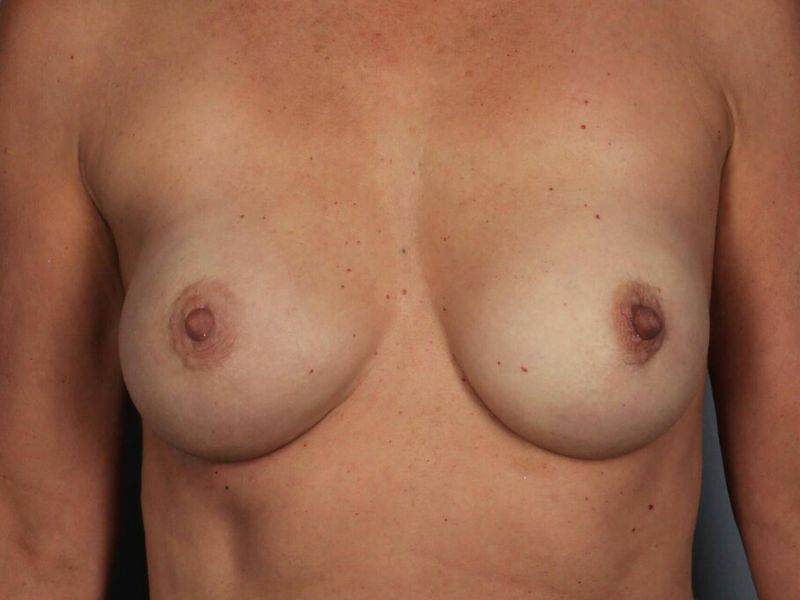
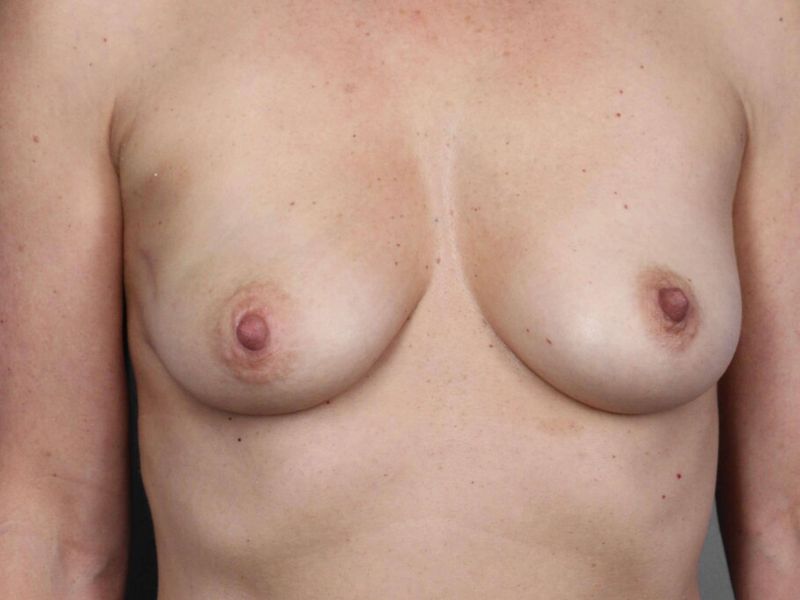
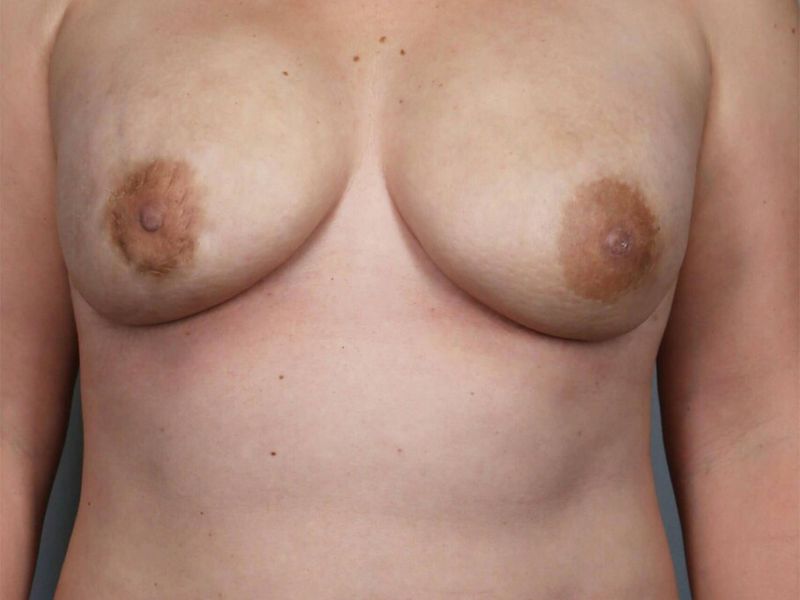
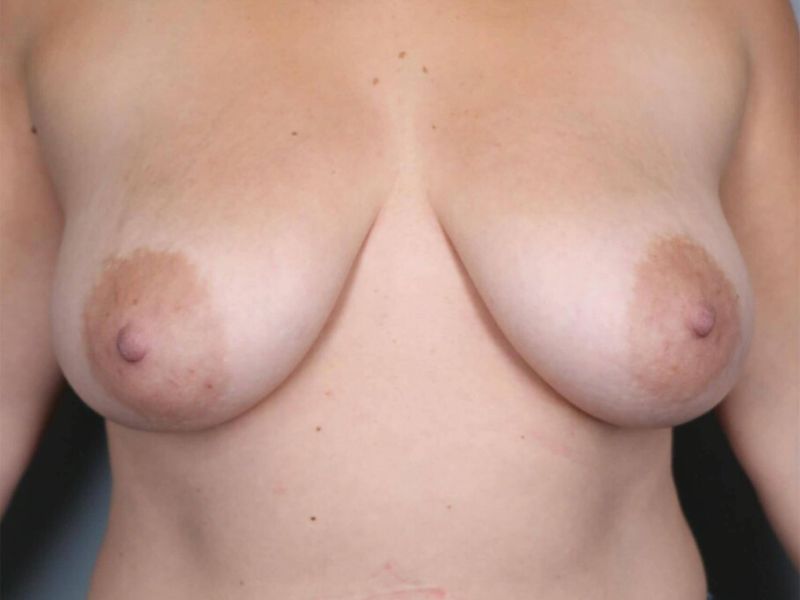
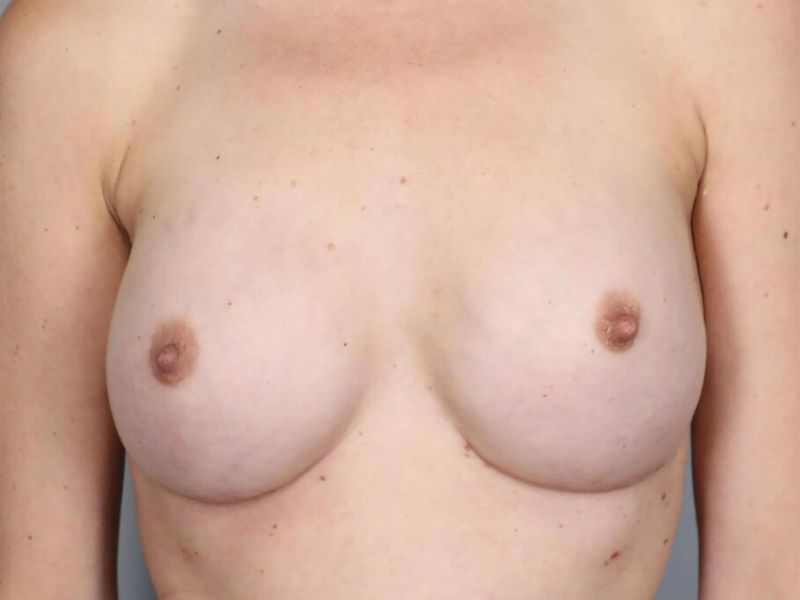
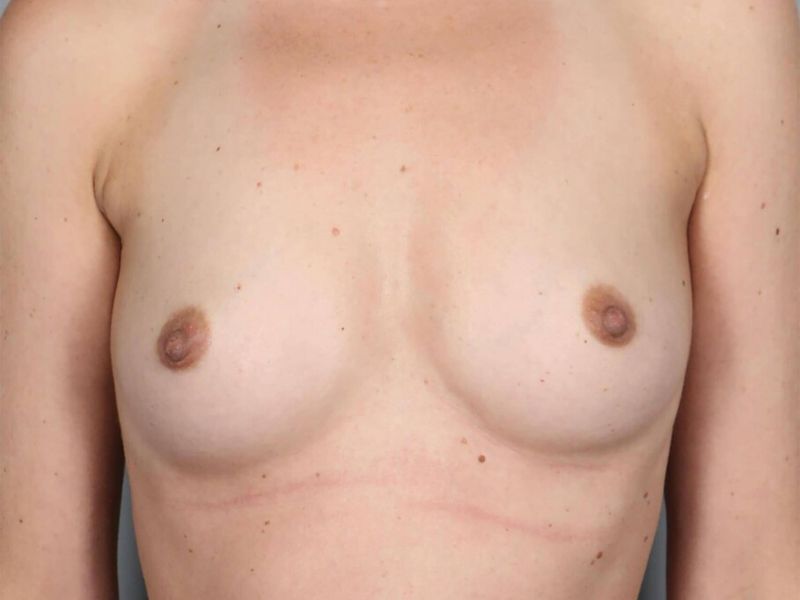
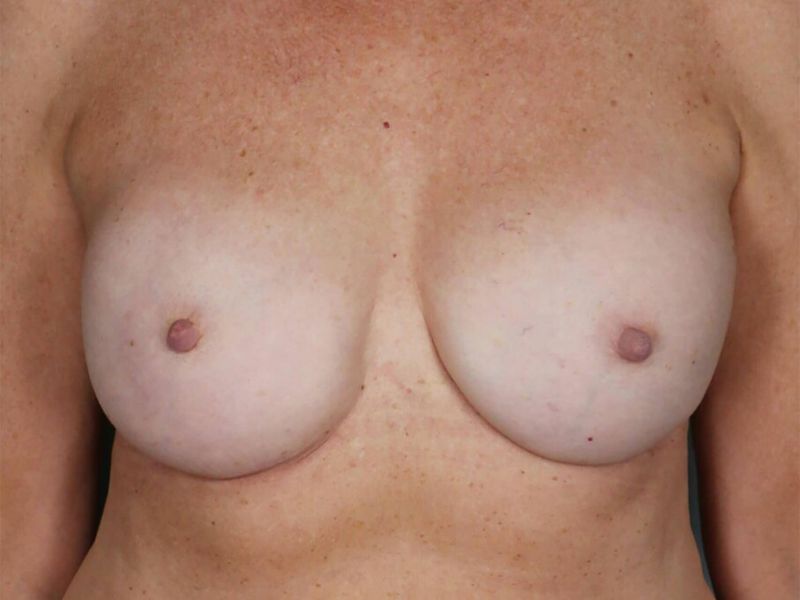
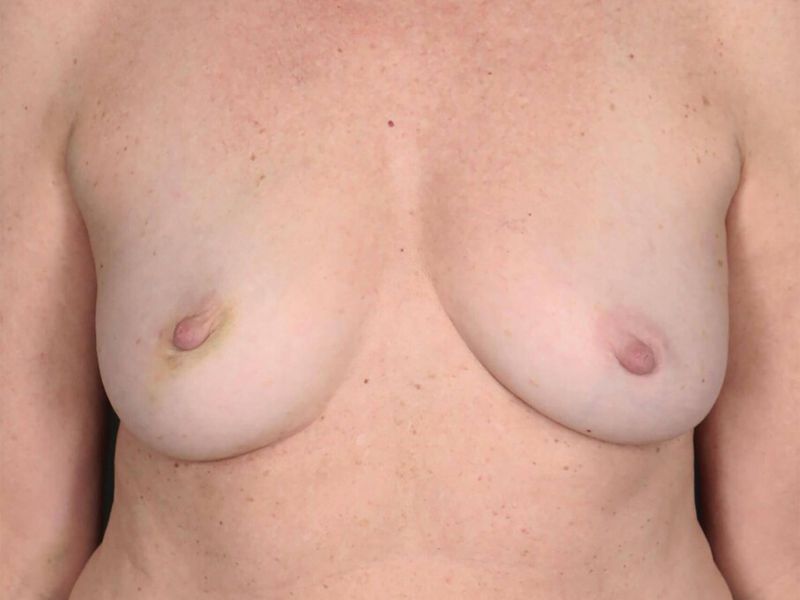


Insurance
Read about coverage & financing →Under federal law, breast reconstruction after mastectomy is billable to insurance. Our team works directly with your provider to handle authorization and approvals.
FAQ
Common questions.
What is direct-to-implant breast reconstruction?
Direct-to-implant, or DTI, breast reconstruction is a one-stage reconstruction in which the permanent breast implant is placed at the time of mastectomy. This avoids the routinely planned tissue-expander stage and the second operation required to exchange the expander for a permanent implant.
Is direct-to-implant reconstruction safer than a tissue expander?
When direct-to-implant reconstruction can be performed safely in one operation, I believe it is inherently preferable to requiring two planned operations. Every additional surgery introduces another exposure to anesthesia, infection risk, bleeding, recovery, time away from normal life, and the possibility of another complication.
Direct-to-implant reconstruction is extremely safe when two conditions are met: the mastectomy skin is well perfused, and the implant fits the mastectomy envelope appropriately. In that setting, the permanent implant can be placed at the time of mastectomy without creating harmful tension on the skin, and the patient avoids the routinely planned second operation required with a tissue expander.
For this reason, in a properly selected patient with a healthy mastectomy flap and an implant that fits the skin envelope correctly, I consider DTI at least as safe as staged expander reconstruction, and potentially safer overall because it accomplishes the reconstruction in one operation rather than two.
A tissue expander still has an important role when the mastectomy skin is genuinely compromised, when the final skin envelope is uncertain, or when the breast cannot be reconstructed safely with a definitive implant at the initial operation.
Can I go larger with direct-to-implant reconstruction?
Yes, in selected patients. The limiting factor is usually the available skin envelope rather than the original breast size. If the skin is sufficiently loose and healthy, an implant larger than the mastectomy specimen can be used. In our study of 499 reconstructed breasts, using an implant larger than the mastectomy specimen did not increase the rate of mastectomy-flap necrosis.
Can women with large breasts have direct-to-implant reconstruction?
Yes. Large breast size alone does not exclude a patient from DTI reconstruction. The more important considerations are the relationship between the skin envelope, nipple position, desired final breast size, and the range of implant sizes available.
Can direct-to-implant reconstruction lift the breast or nipple?
A mild degree of nipple elevation can occur because the weight of the breast tissue is removed and the implant is supported by mesh. In selected patients, the reconstruction can also be designed to help the nipple and skin adhere in a more favorable position. Patients who need a major lift or want to become substantially smaller may need a skin-reducing or lifting reconstruction instead.
What is prepectoral breast reconstruction?
Prepectoral reconstruction places the implant above the pectoralis major muscle rather than underneath it. This avoids detaching the muscle from the chest wall and eliminates the animation deformity that can occur when a subpectoral implant moves or distorts with muscle contraction.
What is Shape Force?
Shape Force is the technique I use to control the contour of the implant with structural mesh rather than simply wrapping the implant uniformly. The mesh can be made narrower and tighter at the upper pole and broader at the lower pole to create a more natural teardrop shape, or it can be adjusted differently for a patient who prefers more upper-pole fullness.
Does direct-to-implant reconstruction mean I will only have one surgery?
DTI eliminates the routinely planned expander-to-implant exchange operation, but it does not guarantee that a patient will never choose or need another procedure. Some patients later choose small refinements such as fat grafting to soften an implant edge, improve contour, or correct asymmetry.
Will I need fat grafting after direct-to-implant reconstruction?
Not necessarily. Some patients are completely satisfied after their initial reconstruction. Fat grafting is most useful when additional soft-tissue coverage, contour smoothing, or correction of a visible implant edge is desired. One of the goals of Shape Force is to create a smoother upper-pole transition during the initial reconstruction.
Can direct-to-implant reconstruction be used if I need radiation?
Yes, and in many patients who are expected to need radiation, I strongly prefer direct-to-implant reconstruction when it can be performed safely. If the mastectomy skin is well perfused and the permanent implant fits the skin envelope appropriately, completing the reconstruction at the time of mastectomy avoids the routinely planned second operation required with a tissue expander.
This becomes particularly important when radiation is anticipated. With a staged reconstruction, the tissue expander often has to be exchanged for a permanent implant after the tissues have already been radiated. That means returning surgically to a field that may be stiffer, less vascular, and less forgiving. Whenever possible, I would rather complete the definitive implant reconstruction before radiation than plan an additional operation through radiated tissue later.
I also strongly prefer placing the implant above the pectoralis muscle when radiation is expected. Subpectoral reconstruction exposes the pectoralis muscle and the implant capsule to radiation and is associated with a higher risk of significant capsular contracture and implant distortion. When the anatomy and mastectomy allow it, prepectoral direct-to-implant reconstruction avoids disrupting the pectoralis and, in my view, provides a better foundation for a patient who will subsequently undergo radiation.
How do you know whether the mastectomy skin is healthy enough for DTI?
The mastectomy skin is assessed clinically and with quantitative SPY-PHI indocyanine-green angiography during surgery. This allows us to visualize blood flow to the skin rather than relying on appearance alone and helps identify areas that may be at increased risk for healing problems.
What happens if the mastectomy skin does not look healthy during surgery?
I assess the mastectomy skin both clinically and with quantitative SPY-PHI indocyanine-green angiography during surgery. If any area has a relative perfusion score below 25%, I consider that skin at increased risk and place the patient into a different postoperative care pathway with closer surveillance and more intensive treatment intended to support flap survival.
A low SPY-PHI score does not automatically mean that I abandon direct-to-implant reconstruction. I have successfully performed DTI in patients with areas of reduced intraoperative perfusion, but the reconstruction must still fit the mastectomy envelope appropriately. I would never knowingly place an implant that creates excessive tension or mechanically compromises an already vulnerable flap, regardless of the perfusion score.
The difference is what happens afterward. Patients with lower perfusion measurements receive intensified postoperative surveillance and a modified treatment pathway, including increased hyperbaric oxygen therapy and other measures directed at supporting threatened mastectomy skin. In our experience, we have had excellent success using this risk-adapted approach, including in patients whose intraoperative perfusion measurements initially placed them in a higher-risk category.
Why do you use mesh in direct-to-implant reconstruction?
Mesh helps support the implant, control its position, and shape the breast. I use it not only as coverage but as a structural element that helps determine where the implant sits and how the final breast contour develops.
How long does a direct-to-implant reconstruction last?
The implant placed during DTI is intended to be the definitive implant rather than a temporary device. Breast implants are not considered lifetime devices, however, and future surgery may be needed if there is an implant-related problem, a change in breast shape, or a patient chooses revision for aesthetic reasons.
Related reading
From the journal.


Sources
Cited research.
- 1Cassileth LB, Kohanzadeh S, Amersi F. One-stage immediate breast reconstruction with implants: a new option for immediate reconstruction. Ann Plast Surg. 2012;69(2):134-138. doi.org
- 2Silva J, Carvalho F, Marques M. Direct-to-Implant Subcutaneous Breast Reconstruction: A Systematic Review of Complications and Patient's Quality of Life. Aesthetic Plast Surg. 2023;47(1):92-105. doi.org
- 3Kalstrup J, Willert CB, Weitemeyer MB, Chakera AH, Hölmich LR. Immediate direct-to-implant breast reconstruction with acellular dermal matrix: Evaluation of complications and safety. Breast. 2021;60:192-198. doi.org
- 4Cassileth LB, Killeen K, York A, Rosen D. Does Breast Implant Size Larger Than Mastectomy Specimen Size Increase the Risk of Flap Necrosis? Aesthet Surg J Open Forum. 2026;8. doi.org
- 5Liu EH, et al. Intraoperative SPY Reduces Post-mastectomy Skin Flap Complications: A Systematic Review and Meta-Analysis. Plast Reconstr Surg Glob Open. 2019. pubmed.ncbi.nlm.nih.gov
- 6Moyer HR, Losken A. Predicting Mastectomy Skin Flap Necrosis with Indocyanine Green Angiography: The Gray Area Defined. Plast Reconstr Surg. 2012. pubmed.ncbi.nlm.nih.gov
- 7Shammas RL, Levy J, Boe LA, et al. Risk of Radiation-Induced Capsular Contracture Following Subpectoral or Prepectoral Implant-Based Breast Reconstruction. Plast Reconstr Surg. 2026;157(1):6e-14e. doi.org
- 8Weissler JM, Banuelos J, Jacobson SR, et al. Intravenous Tranexamic Acid in Implant-Based Breast Reconstruction Safely Reduces Hematoma Without Thromboembolic Events. Plast Reconstr Surg. 2020;146(2):238-245.
- 9Kenna DM, et al. Absorbable Antibiotic Beads Prophylaxis in Immediate Breast Reconstruction. Plast Reconstr Surg. 2018;141(4):486e-492e.
- 10Ahmed S, Hajj JP, VonDerHaar RJ, et al. Prophylactic absorbable antibiotic beads for prepectoral implant-based breast reconstruction: a single institution early experience. J Plast Reconstr Aesthet Surg. 2024;96:107-110.
- 11Kim DY, Park SJ, Bang SI, et al. Does the use of incisional negative-pressure wound therapy prevent mastectomy flap necrosis in immediate expander-based breast reconstruction? Plast Reconstr Surg. 2016;138:558-566.
- 12Chicco M, Huang TCT, Cheng HT. Negative-Pressure Wound Therapy in the Prevention and Management of Complications From Prosthetic Breast Reconstruction: A Systematic Review and Meta-analysis. Ann Plast Surg. 2021;87(4):478-483. doi.org
- 13Chang AJBA, Pinto EAFB, Silva DR, et al. Photobiomodulation in Promoting Increased Skin Flap Viability: A Systematic Review of Animal Studies. Lasers Med Sci. 2024;39(1):109. doi.org
- 14Maghfour J, Ozog DM, Mineroff J, Jagdeo J, Kohli I, Lim HW. Photobiomodulation CME Part I: Overview and Mechanism of Action. J Am Acad Dermatol. 2024;91(5):793-802. doi.org
- 15Rand-Luby L, Pommier RF, Williams ST, Woltering EA, Small KA, Fletcher WS. Improved outcome of surgical flaps treated with topical dimethylsulfoxide. Ann Surg. 1996;224(4):583-589.
- 16Çelen O, Yildirim E, Berberoğlu U. Prevention of wound edge necrosis by local application of dimethylsulfoxide. Acta Chir Belg. 2005;105(3):287-290.
- 17Wiesemann GS, Cox EA, Nichols DS, Spiguel LR, Heath FD, Kanchwala S, Sorice-Virk S. Salvage of Nipple-Areolar Complex Ischemia With Dimethyl Sulfoxide: A Case Series. Ann Plast Surg. 2023;90(1):8-12. pubmed.ncbi.nlm.nih.gov
- 18Baynosa RC, Zamboni WA. The effect of hyperbaric oxygen on compromised grafts and flaps. Undersea Hyperb Med. 2012;39(4):857-865.
- 19Francis A, Baynosa RC. Hyperbaric Oxygen Therapy for the Compromised Graft or Flap. Adv Wound Care (New Rochelle). 2017;6(1):23-32.
- 20Rajpal N, Walters ET, Elmarsafi T, Pittman TA, Johnson-Arbor KK. Use of hyperbaric oxygen therapy for tissue ischemia after breast reconstruction. Undersea Hyperb Med. 2019;46(4):461-465.
Ready to discuss direct-to-implant breast reconstruction?
Schedule a consultation with Dr. Cassileth and her team to explore your options.
Request a consultation